
The next major CMS-0057-F compliance milestone is quickly approaching. As of September 2026, CMS has not announced a broad extension of the rule’s API requirements, which generally take effect January 1, 2027, although exact applicability varies by payer type and plan year.
Recent CMS resources have moved the conversation from regulatory requirements to practical implementation. New workflow guidance and a more detailed public-reporting template reinforce an important point: compliance requires more than standing up an API endpoint. Payers need an operational infrastructure capable of returning plan-specific requirements, accepting clinical documentation, processing requests and communicating actionable decisions.
Several Requirements Are Already in Effect
CMS-0057-F is often discussed as a 2027 mandate, but several requirements took effect January 1, 2026. Impacted payers must now:
- Issue standard prior authorization decisions within seven calendar days.
- Issue expedited decisions within 72 hours.
- Provide a specific reason when denying a request, regardless of how it was submitted.
- Publish prior authorization performance metrics annually on a publicly accessible website.
- Report annual Patient Access API usage metrics to CMS.
The seven-day standard decision timeframe does not apply to Qualified Health Plan issuers on federally facilitated exchanges under this rule, although other applicable requirements may. CMS-0057-F also excludes prior authorizations for drugs.
CMS’s latest reporting guidance clarifies that public metrics cannot be available only through a password-protected member or provider portal. Payers should publish an understandable list of services requiring prior authorization, not simply a list of procedure codes, and clearly report approval, denial, appeal and turnaround-time measures. Review the CMS reporting guidance and template.
What Must Be Ready for 2027
Beginning January 1, 2027, impacted payers generally must support four interconnected capabilities:
Prior Authorization API
The API must indicate whether authorization is required, identify payer-specific documentation requirements, accept requests and return approvals, denials, requests for additional information and authorization expiration details.
Provider Access API
Payers must share claims, encounter, clinical and prior authorization data with in-network providers that have a treatment relationship with the member. This capability also requires provider attribution, member opt-out processes and plain-language educational materials.
Payer-to-Payer API
Payers must support the exchange of up to five years of relevant member data when coverage changes, subject to the member’s consent. This requirement includes operational processes for identifying previous and concurrent coverage, managing opt-ins and incorporating received data into the member record.
Expanded Patient Access API
Specified prior authorization information must be added to the data already available through the member-facing Patient Access API.
Impacted payer categories include Medicare Advantage organizations, state Medicaid and CHIP fee-for-service programs, Medicaid and CHIP managed care organizations, and issuers offering individual-market Qualified Health Plans on federally facilitated exchanges. A commercial health plan is not automatically subject to CMS-0057-F simply because it offers employer-sponsored coverage.
Where Payers Should Focus
With only months remaining, the greatest risk is treating compliance solely as an integration project instead of an operating-model transformation. An API can open the digital front door, but it cannot by itself resolve the payer-side complexity behind each prior authorization request. Plans still need current benefit logic, product and employer-group variations, medical-policy alignment, documentation requirements, escalation paths, denial-reason workflows, provider communications and downstream claims coordination working as one connected process.
If those operational dependencies remain disconnected, payers may meet a technical milestone while still producing inconsistent determinations, avoidable rework and provider abrasion. The organizations that will be best prepared for 2027 are the ones using this deadline to strengthen governance, connect authoritative payer logic to every transaction and turn interoperability into a reliable operational capability rather than a standalone IT deliverable.
That shift requires more than technical readiness. It requires a deliberate operating plan for the decisions, workflows and accountability that sit behind every transaction.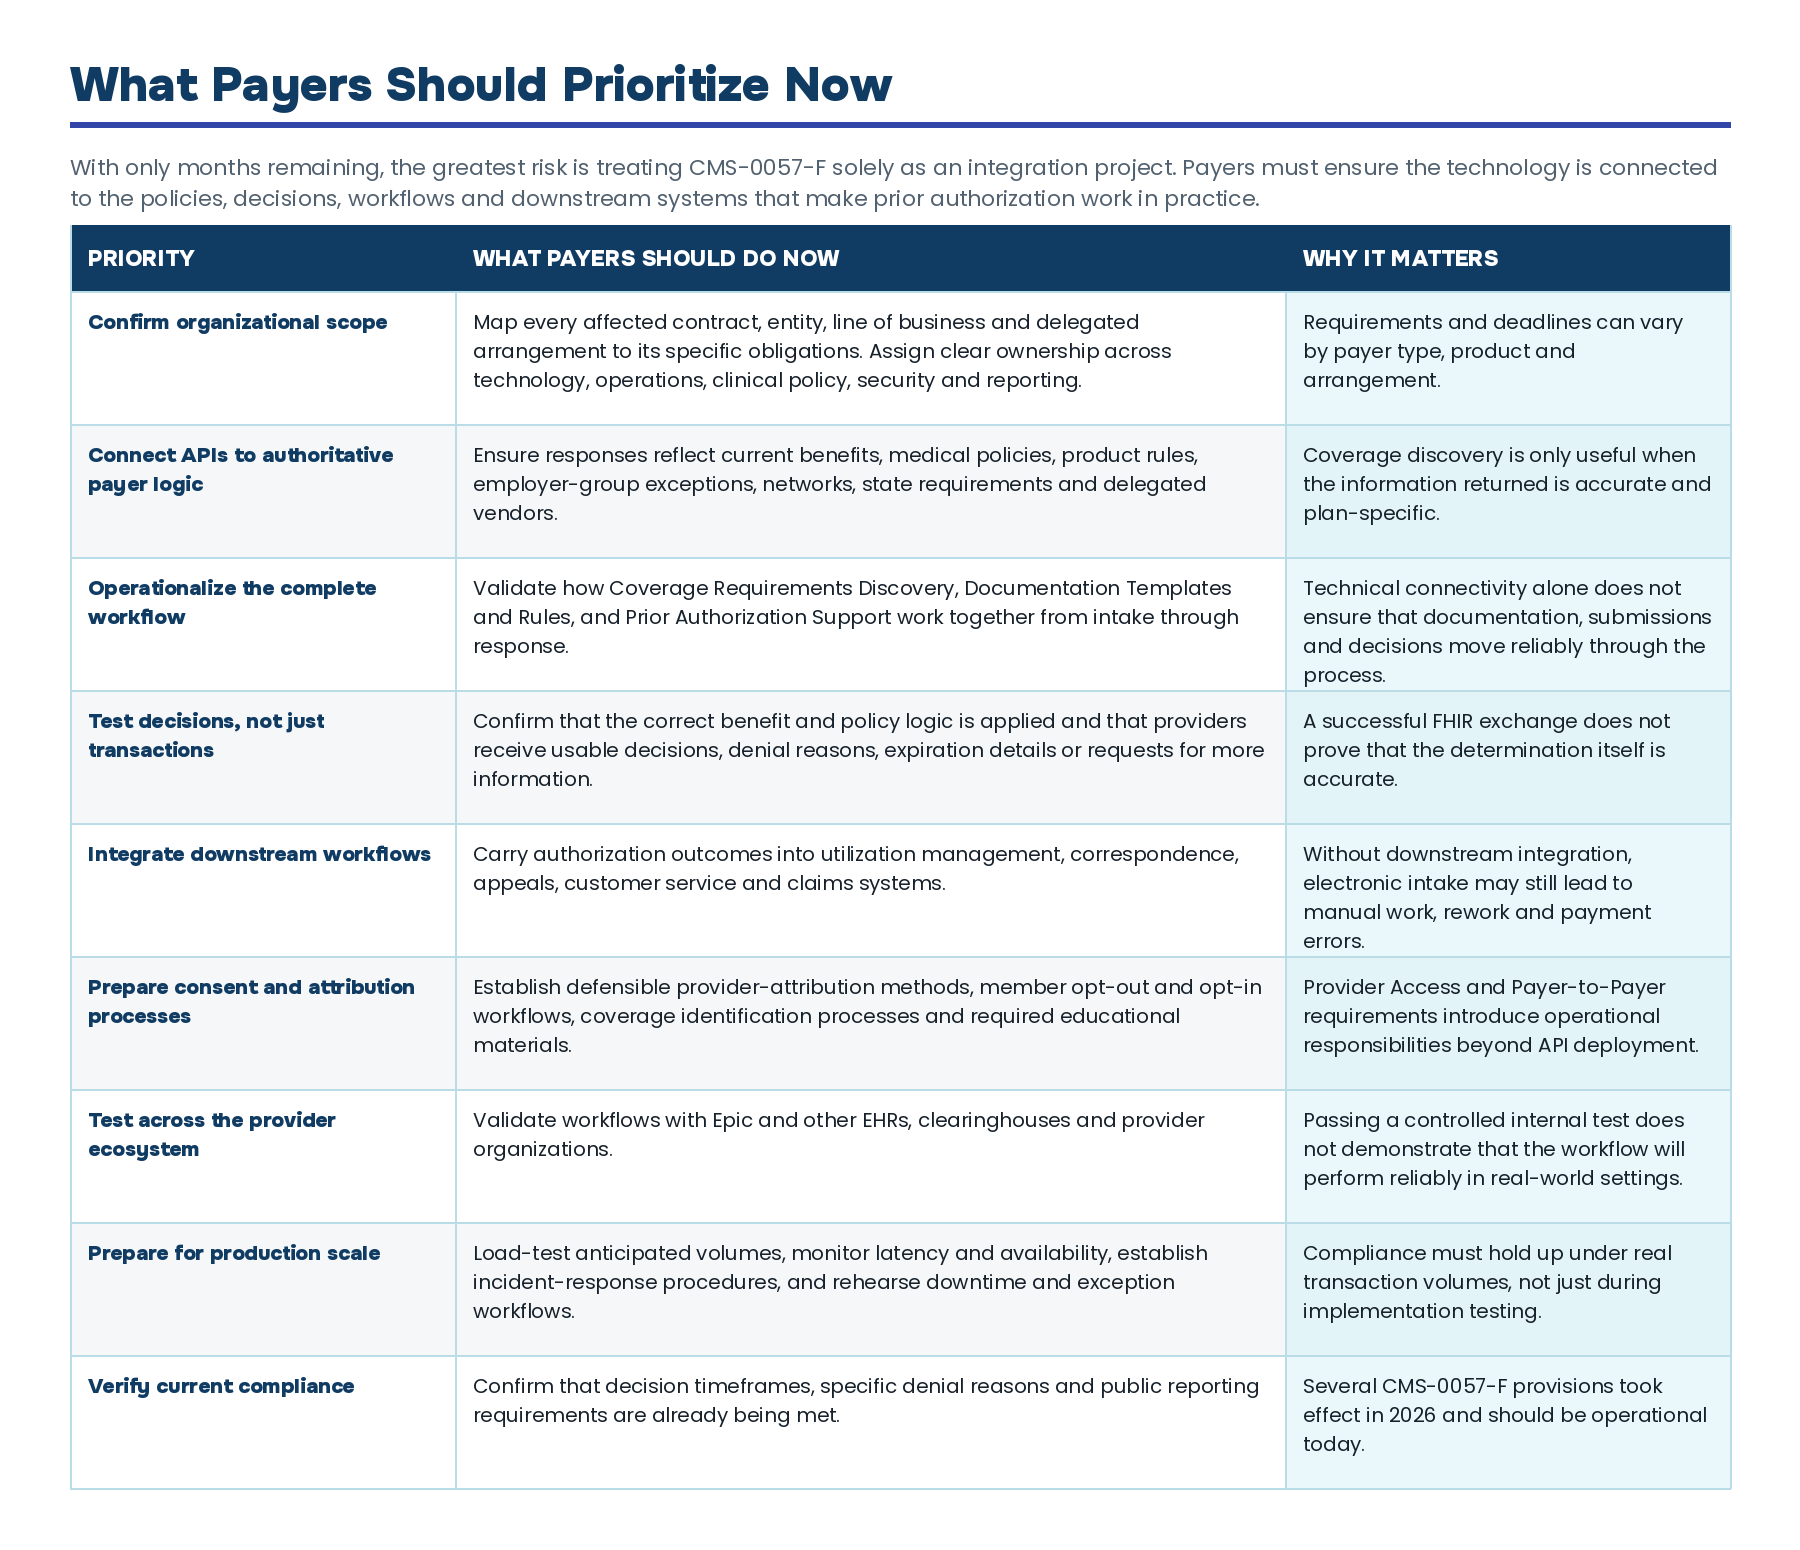
The API Is the Front Door, Not the Entire Operation
CMS-0057-F is creating an essential digital front door for prior authorization. But opening that door does not determine what happens once a request enters the payer environment.
Behind the API, health plans still must interpret benefits and medical policies, apply product and employer-group variations, manage exceptions, preserve clinical oversight, generate compliant communications and carry accurate decisions into claims.
Payers that focus only on connectivity may satisfy the technical requirement while leaving the underlying complexity untouched. Those that use CMS-0057-F to modernize the complete payer-side operation have a greater opportunity to improve provider experience, reduce administrative burden and make faster, more consistent authorization decisions at scale.
Vital Data Technology helps health plans move CMS-0057-F beyond connectivity and into day-to-day operational performance. By linking real-time data exchange to benefit logic, medical policy and clinical intelligence, VDT helps plans return more accurate determinations, support clearer provider interactions and carry decisions cleanly into the workflows that follow. With instant decisioning, configurable payer workflows and experience across complex products, employer groups and care settings, VDT helps modernize not just the digital front door, but the authorization operation behind it.
For the complete regulatory requirements, review the CMS Interoperability and Prior Authorization Final Rule overview.

Recent Posts
- The CMS-0057-F Deadline is Approaching: What Payers Need to Know Now
- Vital Data Technology Achieves AMP Measure Certification for 2026, Marking Sixth Consecutive Year
- From Decisions to Outcomes: Building the Agentic Health Plan
- Beyond Automation: The Agentic Operating Model for Health Plans
- The Growing Use of AI Agents in Health Plan Clinical Workflows
Archives
Categories
- intelligent automation
- Quality Improvement
- Artificial Intelligence
- Care Management
- AI
- Data Science
- Utilization Management
- HEDIS
- Industry Insight
- Intelligent Prior Authorization
- News
- Population Health
- Healthcare Payer
- Agentic AI
- Predictive Models
- Risk Adjustment
- Medicare Advantage
- NCQA
- Predictive Analytics
- Prior Authorization
- AI Agents
- CMS-0057-F
- Behavioral Health
- Interoperability
- Medicare
- Payer Industry Trends
- Social Determinants of Health
- Value-Based Care
- AMP Certification
- Appeals & Grievances
- COVID
- Cloud-Native Platform
- Care Gaps
- CareFlow Intelligence
- Compliance
- FHIR
- Gen AI
- Insights
- Rules Engine
- Staffing Ratios
- Star Ratings
- Aii
- Cloud native
- HEDIS Measurement Year 2026
- Integration
- Medical Loss Ratio
- Medical Management
- Member Engagement
- Provider Engagement
- Regulations
- TPAs
Subscribe to Our Newsletter

Vital Data Technology is transforming the healthcare ecosystem by empowering healthcare stakeholders with prescriptive insights to improve member health and lower costs. Vital Data Technology leverages embedded, real-time data science, AI, and analytics together to drive intelligent automation through their cloud-based Affinitē platform.
Follow Us
Address
800 Newport Center Drive, Suite 450
Newport Beach, CA 92660